Archive for category: Useful Information

Did you know that until recently the CDC had on their website that vaccines were proven to not cause autism and that the whole issue had been totally debunked with mountains of studies and scientific evidence? Well, last fall, the CDC changed that statement explaining that there actually was NO evidence that vaccines were safe from causing autism. Why did they change their tune? It’s because Aaron Siri sued the CDC, deposed all of their vaccine experts, and forced them admit the truth – there is no mountain of evidence, collection of studies, and no thorough debunking. In fact, there is not a single study showing infant vaccines do not cause autism. In his book, Vaccines, Amen, Aaron Siri does an excellent, thorough job reviewing all the pertinent vaccine data to date. He has literally reviewed every pertinent study. How many physicians can say the same thing? He correctly points out that in regard to the “all vax all the time” crowd, we are dealing with a bunch of fervent vaccine believers, “impervious to reason or data, even when it is provided from their oracle, the CDC.” I highly recommend everyone interested in the truth read this book. However, be warned. As Mr. Siri is known to say, once you see it, you can’t unsee it…

None of the vaccines currently given to young children have ever been tested for safety in a saline-placebo controlled trial. As a clinical immunologist, I was shocked to learn this fact 4 years ago. I highly recommend this book as it details the history of the vaccine industry from its infancy to modern times.

Big Pharma may be evil, but it is not stupid. It has tons of money and knows how to use it. It knows an important way to influence physicians is to control what they read. In 2024, both JAMA and BMJ published studies revealing that the majority of peer reviewers for JAMA, BMJ, Lancet, and NEJM, the four journals with the highest circulation, receive payments from Big Pharma. From 2020-2022, they received $1.06 billion. Both articles state the obvious – that this is a dangerous conflict of interest. Add to that the amount of money these journals receive from Big Pharma advertising, and one can see the corresponding end result.

https://jamanetwork.com/journals/jama/fullarticle/2824834

https://www.bmj.com/content/387/bmj.q2260.full

In August 2004, Marcia Angell, MD published her book, The Truth About The Drug Companies: How They Deceive Us And What To Do About It.

She joined the editorial staff of NEJM in 1979, became executive editor in 1988, and became the first woman editor in chief of the journal in 1999. In this book, Dr. Angell details the tricks Big Pharma commonly uses to make their drugs look safer than they really are and to make them appear more effective than they really are. This book was supposed to be a warning and a call to action. Unfortunately, her wake up call went unheeded. Like most physicians, I used to think a study printed in one of these top journals represented the epitome of science. How sad and depressing to realize many are actually the complete opposite – propaganda bought and paid for by Big Pharma.

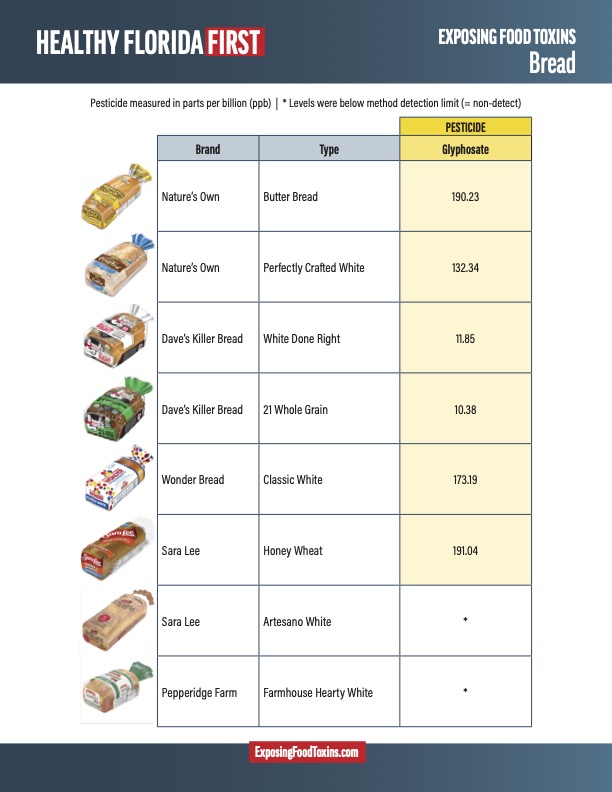
In early February, the state of Florida released their test results of popular brands of bread for glyphosate (herbicide) levels. Some people who have been diagnosed with a gluten allergy/intolerance may actually have glyphosate allergy/intolerance.

Although the organic brand, Dave’s Killer Bread, did well, the only two with undetectable levels were Sara Lee’s Artesano White and Pepperidge Farm’s Farmhouse Hearty White. The next time you are in the grocery store, try one of these glyphosate free options.

The corrupt actions of Big Pharma have been going on for a long time. Dr. Kory does a masterful job of telling the story of how chlorine dioxide was placed on Big Pharma’s “hit list” decades ago, and how they were ready for it at the start of COVID. When one reviews the evidence of how effective chlorine dioxide is, it’s not a surprise. I highly recommend everyone read this book. You can get a copy at this link. waronchlorinedioxide.com.

An article, COVID-19 mRNA Vaccination and 4-Year All-Cause Mortality Among Adults Aged 18 to 59 Years in France, was published in JAMA Network Open on December 5, 2025 making it look like all-cause mortality was lower in people who got the COVID shot compared to those who did not. The main stream press started reporting on it late last week. I obtained this study and planned on posting my critical analysis of it – but someone beat me to it.

Ian Miller, in his article, No, This Viral Study Doesn’t Prove The COVID Vaccine Worked To Prevent Deaths, published on December 18, 2025, does an excellent job analyzing the above paper and pointing out all of its misleading nonsense. Here are a few of the absurd findings in this study. If we are to believe this data, then COVID shots prevent death from transportation crashes, falls, drownings, unintentional injuries and even mental disorders…! All anyone has to do is actually read this paper to know its results are meaningless. This is utter dishonesty, pure and simple.

Well, here’s another one, published in early November 2025. “Vascular and inflammatory diseases after COVID-19 infection and vaccination in children and young people in England: a retrospective, population-based cohort study using linked electronic health records“

This pediatric study makes it look like COVID infection has higher risks for certain vascular and inflammatory diseases compared to Pfizer COVID shots.  Not surprisingly, main stream news covered this study with article titles like, “New data show COVID-19 infection much worse for children than the vaccine.”  

Let me say that this paper is a classic example of how to manipulate a study so it seems to show whatever you want to show.

Let’s critically analyze this study, shall we?  

First, this is a retrospective, observational study.  Such studies are quite easy to manipulate compared to a placebo controlled, prospective study.  When written by unprincipled authors, the results are essentially worthless.  

Next, this study specifically addressed 5 conditions: arterial clots, venous clots, thrombocytopenia, myocarditis/pericarditis, and inflammatory conditions like Kawasaki’s Disease.  There are a whole host of known side effects, why specifically these five?

This study looked at a snap shot in time, focusing on side effects after the first infection.  Then it looked at another snap shot from a different time, focusing on side effects after the first shot.  Why look only at the first infection and first shot?  Wouldn’t it be more relevant to the real world to look at what happens after the second, third, and forth infections and shots?

The time period of study was different between the infection group and the shot group.  The infection group was studied from January 1, 2020 to March 31, 2022.  The shot group was studied from August 6, 2021 to December 31, 2022.

The age of the patients in the two groups were different.  The infection group included newborns up to 18 years of age.  The shot group included children age 5 up to 18 years go age.  The shot group did not include children below the age of five.

These discrepancies should stand out as a red flag to the honest reader.  The time period of study should be the same between both groups.  The age of the patients should be the same in both groups.  Yet, they were not.

Why would the time period of study make such a big difference?  Recall that COVID was most severe with the original, Wuhan version, and then became less and less severe with each subsequent variant.  The Wuhan version dominated until late spring 2021.  Then the delta variant took over from early summer 2021 through November 2021.  Then the omicron variant appeared in late 2021 and dominated 2022.  The delta variant was significantly less severe than the Wuhan version both in terms of morbidity and mortality.  Following suit, the omicron variant was significantly less severe than the delta variant.  The bottom line is the infection group included the most severe and deadliest time span, the Wuhan period, and the shot group did not.  There is no doubt that had the infection group had the same time span as the shot group, the results would have been the opposite, demonstrating a higher risk of side effects for the shot group.

The Pfizer shot group did not include children under the age of 5 and this study looked specifically at arterial clots, venous clots, thrombocytopenia, myocarditis/pericarditis, and inflammatory diseases like Kawasaki’s Disease.  Let’s look at the age distribution of these diseases.  It turns out that both arterial and venous clots occur most often in infants and teens.  Thrombocytopenia occurs most often in infants and toddlers.  Myocarditis/pericarditis occur most often in infants and teens.  And Kawasaki’s Disease occurs most often in children 5 and under.  Thus, by not including the under 5 years of age children, it automatically skewed the results in favor of the shot group.  

Cherry picking?  Comparing apples to oranges?  Deception?  Lies?  Such is the playbook for the Pro-Clot-Shot crowd.  This paper is crap.  And so are its authors.

On Wednesday October 8, 2025, my news feed contained an article about how the latest New England Journal of Medicine study found COVID shots to be effective in veterans. I obtained this study and analyzed it. As I suspected, this study had the same flaws found in most other such studies. The duration of this study was only 6 months. As I have already commented on previous posts, the study from Qatar by Chemaitelly et al. demonstrated that the mild improvement in COVID shot effectiveness (46.6% in their study) that occurs early on plummets in a linear fashion, turning NEGATIVE 5-6 months after shot administration. By 7-8 months, the effectiveness was -17.8.

Duration of mRNA vaccine protection against SARS-CoV-2 Omicron BA.1 and BA.2 subvariants in Qatar Hiam Chemaitelly 1,2,3✉, Houssein H. Ayoub 4, Sawsan AlMukdad1,2, Peter Coyle 5,6,7, Patrick Tang 8, Hadi M. Yassine 6,9, Hebah A. Al-Khatib6,9, Maria K. Smatti6,9, Mohammad R. Hasan8, Zaina Al-Kanaani5, Einas Al-Kuwari5, Andrew Jeremijenko 5, Anvar Hassan Kaleeckal5, Ali Nizar Latif5, Riyazuddin Mohammad Shaik5, Hanan F. Abdul-Rahim10, Gheyath K. Nasrallah 6,9, Mohamed Ghaith Al-Kuwari11, Adeel A. Butt 3,5,12, Hamad Eid Al-Romaihi13, Mohamed H. Al-Thani13, Abdullatif Al-Khal 5, Roberto Bertollini13 & Laith J. Abu-Raddad 1,2,3,10✉ https://pubmed.ncbi.nlm.nih.gov/35654888/ https://doi.org/10.1038/s41467-022-30895-3

Had the Chemaitelly study been extended, who knows how low it would have gone. So you see, by only looking at the first 6 months, you are getting a false impression of the shot’s performance. It’s dishonest and misleading.

Poor duration and timing selection can also be used the other way, making something look worse than it really is. For example, let’s take anti-virals. Anti-viral treatments work best when administered early on because that is when viruses replicate the most. Each day the treatment is delayed, it becomes less effective. Most are not recommended after 5-7 days of symptoms. So what if a group of scientists tried to study the effectiveness of potential anti-viral COVID treatments but only in hospitalized patients that have been sick for over 7-10 days…? Does that make any sense to you? No. Of course it does not. But that is exactly what happened early on during COVID.

Another problem I found in the NEJM study was ALL participants had to have received a COVID shot in the 2023-2024 season. Why is this a problem? As I have commented in previous posts, the more COVID shots one receives, the worse off they are. The Cleveland Clinic study clearly shows that each additional shot increases risk of COVID infection.

If participants with few or zero COVID shots were allowed into this study, they would have performed the best, revealing that the COVID shot group actually had an increased risk of infection compared to the control. By requiring all participants to have a COVID shot the year before, they diminished that potential problem.

1-year risks of cancers associated with COVID-19 vaccination: a large population-based cohort study in South Korea

Hong Hin Kim, Min-Ho Kim, Myeong Geun Choi, Eun Mi Chun, September 2025

This large-scale population based study was done in Seoul, South Korea with data from 2021 through 2023 involving 8.4 million people.

Overall risk of cancer was 27% higher in vaccinated vs. unvaccinated (HR 1.27, 95% CI 1.21-1.33).

Lung cancer risk increased by 53% (HR 1.53, 95% CI 1.25-1.87).

Prostate cancer risk increased by 69% (HR 1.69, 95% CI 1.35-2.11).

Thyroid cancer risk increased by 35% (HR 1.35, 95% CI 1.21-1.52).

Stomach cancer risk increased by 34% (HR 1.34, 95% CI 1.13-1.58).

Colorectal cancer risk increased by 28% (HR 1.28, 95% CI 1.12-1.47).

Breast cancer risk increased by 20% (HR 1.20, 95% CI 1.07-1.34).

Vaccine Platform

cDNA vaccines (eg. AstraZenica) increased overall risk of cancer by 47% (HR 1.47, 95% CI 1.39-1.56).

mRNA vaccines (eg. Pfizer/Moderna) increased overall risk of cancer by 20% (HR 1.20, 95% CI 1.14-1.26).

Mixed schedules increased overall risk of cancer by 34% (HR 1.34, 95% CI 1.21-1.48).

Booster Dose Risk

Booster doses increased the risk of stomach cancer by 23% (HR 1.23, p=0.041).

Booster doses increased the risk of pancreatic cancer by 125% (HR 2.25, p<0.001).

Overall Trends

All demographic groups, including young adults, had a higher incidence of cancer. The mean age of individuals in this study was 44yo.

Men had a higher risk for stomach and lung cancers.

Women had a higher risk for thyroid and colorectal cancers.

https://pubmed.ncbi.nlm.nih.gov/41013858

https://biomarkerres.biomedcentral.com/articles/10.1186/s40364-025-00831-w

Millions of people today are suffering from Long COVID and COVID Shot Injury. Unfortunately, many hospital affiliated physicians are ignorant of the underlying causes or in complete denial that COVID Shots have any side effects at all. Thus, they are at a loss as to how to truly help their patients. The key to treating Long COVID and COVID Shot Injury is to understand the underlying problem in both – the spike protein.

Spike protein is the part of the SARS-CoV-2 virus that attaches to and infects human cells. It is incredibly toxic to the human body resulting in massive inflammation, broad scale antibody production, and microscopic clots, just to name a few of its effects. It’s the reason COVID was so deadly in its initial form. The mRNA shots that most people received codes for this spike protein. This genetic material spreads throughout all of our organ systems and turns our own cells into spike protein factories. Then our immune system comes into contact with the spike protein, makes antibodies to it, and that is what they hoped would save the day – that these anti-spike antibodies would prevent you from getting COVID, spreading COVID, and get us out of the pandemic. Well, as you can see in the data from my previous posts, it was a total disaster. Not only did they not prevent COVID, they made it more likely to get COVID. Further, they were incredibly dangerous with side effects including myocarditis, heart attack, stroke, turbo cancers, and blood clots.

The key to treating Long COVID and COVID Shot Injury is to mitigate the spike protein and its toxic effects. In my opinion, the two best treatment protocols for this immense problem are the protocols from Independent Medical Alliance developed by a team of physicians led by Paul Marik, MD and Pierre Kory, MD, and the McCullough Protocol developed by Peter McCullough, MD. I have had the honor to personally meet all three of these incredible physicians and have successfully used their protocols in treating thousands of patients over the past 4 years.

As the veil of censorship and ignorance is slowly lifted, it is my hope that all of our colleagues join us in fighting this pre-eminent problem of our time.

Copyright © 2018-2021 - Park Allergy Center, PC